Posterior Placenta Meaning: Position, Impact & What It Means for Pregnancy
September 22, 2026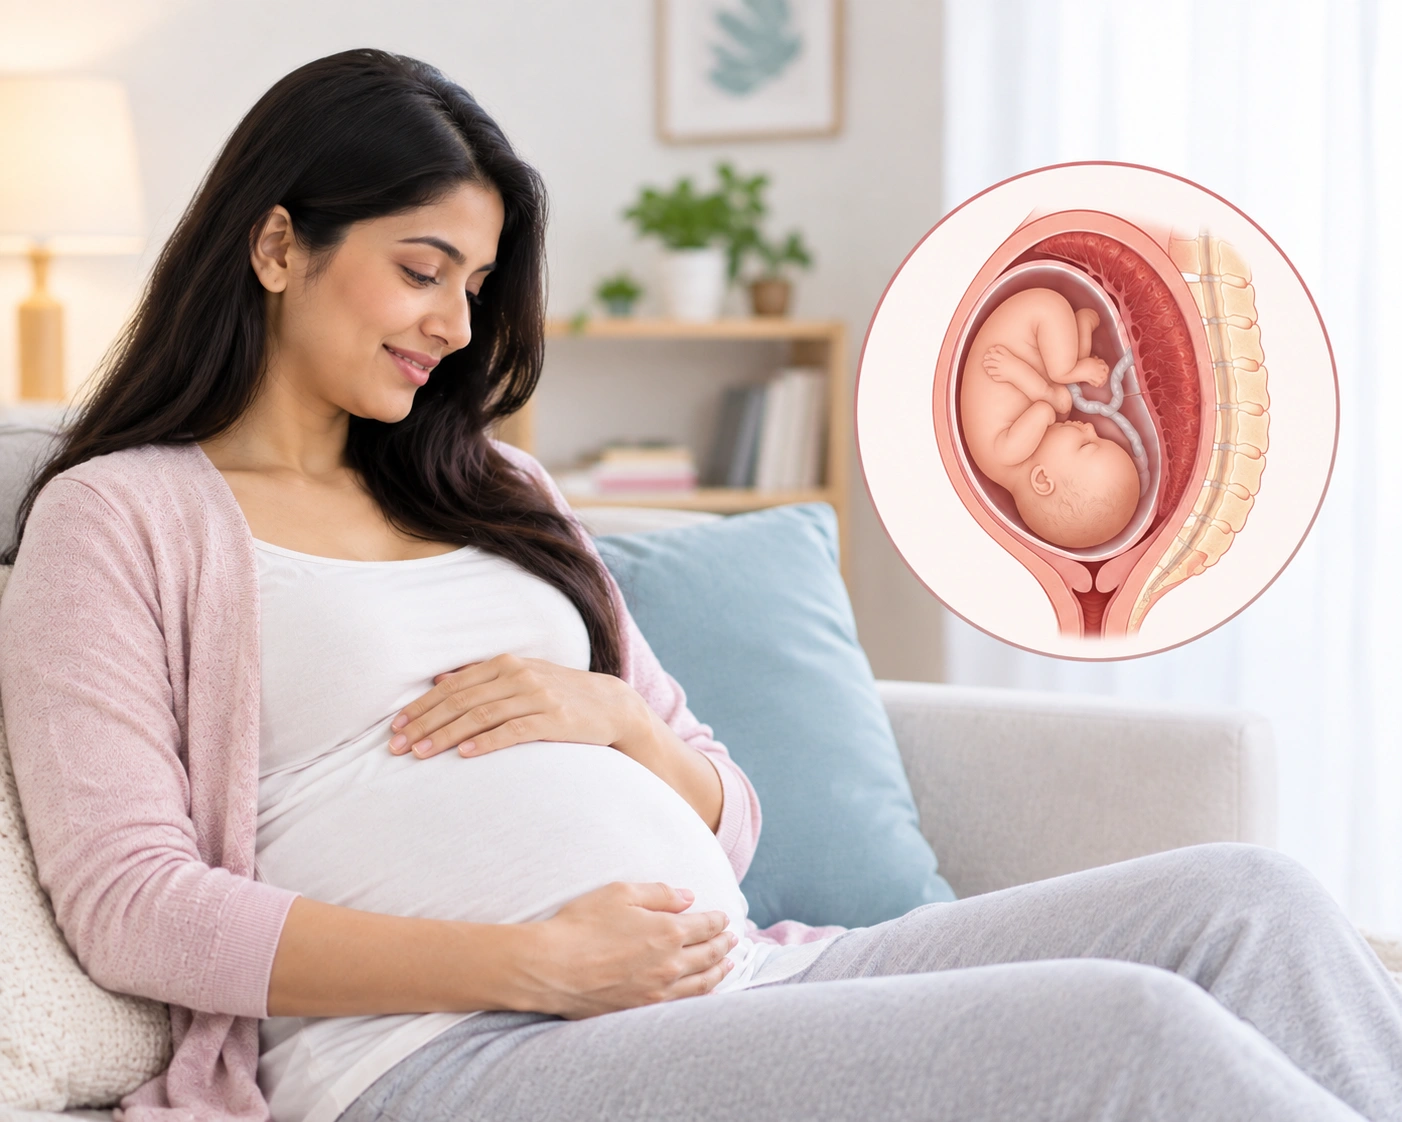
You spot an unfamiliar term on your ultrasound report and, naturally, you Google it before you even ask your doctor. "Posterior placenta" is one of those phrases. It sounds clinical and a bit alarming, but for most women, it's simply describing where the placenta has attached itself, and nothing more.
So what does it actually mean, and should you be worried? Let's break it down. But first, let’s understand the meaning of posterior placenta.
What Is a Posterior Placenta?
The placenta is the organ that forms during pregnancy to keep your baby fed with oxygen and nutrients. It can attach to almost any part of the uterine wall, and where it lands depends on where the fertilised egg settles.
A posterior placenta means it has attached to the back wall of the uterus, the side closer to your spine. It's one of the most frequently seen positions, right along with anterior (front wall), fundal (top), and lateral (side) attachment. There's no real pattern behind it. It's mostly down to chance, not anything you did differently.
Where Is a Posterior Placenta Located?
Think of the uterus as a pouch with two main sides, a front wall facing your belly button and a back wall facing your spine. A posterior placenta sits on that back wall.
But because there's less tissue cushioning things, many women with a posterior placenta feel their baby's kicks and rolls a little earlier than they might otherwise. Your doctor will usually confirm the exact position during the anomaly scan, typically performed between 18 and 22 weeks, though it can sometimes be spotted earlier.
Is a Posterior Placenta Normal?
Completely. If anything, doctors often consider it one of the more favourable positions to have. Blood flow to the baby tends to be good, labour isn't affected, and on its own, it rarely leads to any complications.
What your doctor will actually keep an eye on, no matter which wall the placenta sits on, is whether it's lying too low near or over the cervix. That's called placenta previa, and it's tracked completely separately from anterior or posterior positioning. If it comes up, you'll simply have a follow-up scan later on to check things again.
Posterior Placenta vs Anterior Placenta
Both are common, both are considered normal, and neither one is "better" medically. Still, a few practical differences are worth knowing about.
With a posterior placenta, movements often feel clearer and a bit earlier, since there isn't as much tissue between your baby and your belly. An anterior placenta, on the other hand, sits at the front and can act like a cushion, so those first flutters might feel fainter or take longer to notice.
There's a small imaging difference too. Sonographers sometimes get a slightly clearer view of the heartbeat and facial features when the placenta is posterior, simply because it isn't sitting directly in the scanning path the way an anterior one can.
As for labour and delivery, neither position changes much. What actually matters for delivery outcomes is whether the placenta is anywhere near the cervix, not which wall it happens to be on.
Understanding Posterior Placenta Grades
You might also come across placental "grading," from Grade 0 up to Grade 3 (or III). This has nothing to do with whether the placenta is anterior or posterior. Instead, it describes how the placenta looks on ultrasound as pregnancy progresses, particularly changes in its texture and the degree of calcification.
- Posterior Placenta Grade 0: Usually has a relatively smooth, uniform appearance on ultrasound and is generally seen earlier in pregnancy.
- Posterior Placenta Grade 1: Shows mild changes in placental texture and may appear as pregnancy progresses.
- Posterior Placenta Grade 2: Shows more pronounced changes and areas of calcification, and is more commonly seen later in pregnancy.
- Posterior Placenta Grade 3: Represents a more mature-looking placenta with more prominent calcification, often seen later in pregnancy, including around term.
There's no fixed week when a particular grade is supposed to show up, and maturation varies quite a bit from one pregnancy to the next. Grading is simply a description of how the placenta looks on ultrasound. It doesn't, on its own, measure how well the placenta is actually functioning.
A posterior placenta can move through any of these grades, exactly like an anterior one would. Position and grade are two separate findings on your scan, and one doesn't tell your doctor anything about the other.
How Is a Posterior Placenta Diagnosed in Pregnancy?
You'll usually find out during a routine ultrasound, most often the anomaly scan around the 18- to 22-week mark. While checking the baby's growth, organs, and development, the sonographer also maps exactly where the placenta has attached.
If there's any reason to keep tracking its position, say, to rule out a low-lying placenta, your doctor may schedule a follow-up scan later on. At Apollo Cradle, our top gynaecologists in Bangalore check placental position as part of routine prenatal scans, so most women get this information without needing to book anything extra.
When Should You Consult Your Doctor?
On its own, a posterior placenta in pregnancy rarely needs any special attention beyond your usual checkups. However, call your gynaecologist doctor if you notice:
- Vaginal bleeding or spotting, at any point during pregnancy
- Abdominal pain that's severe or won't let up
- A drop in how often you're feeling the baby move
- Any indication from your scans that the placenta might be sitting low
- Anything that just feels off to you, even if you can't quite explain it
Conclusion
A posterior placenta is about as ordinary as pregnancy findings get. It usually means good blood flow, no real impact on delivery, and absolutely no connection to your baby's sex. What matters far more is keeping up with your regular prenatal visits, so your doctor can look at the full picture rather than fixating on where the placenta happens to sit.
Generally, yes. It's considered a favourable position, tends to support healthy blood flow, and isn't linked to any added risk.
No. Risk usually comes down to other factors, like the placenta lying too low or covering the cervix, not simply whether it's anterior or posterior.
Neither, really. Both positions are normal and common. The differences you'll notice are practical ones, like when you first feel movement or how clear the ultrasound images are, not anything to do with safety or outcome.
Our Doctors

DR. ANITHA M
MBBS, DRNB Plastic S...
| Experience | : | 8 Years |
|---|---|---|
| Speciality | : | Plastic Surgeon/Gyna... | Location | : | Rajajinagar |
| Timings | : | Mon - Sun : 2:00 PM ... |

DR. MANEESHA SINGH
MBBS, DGO...
| Experience | : | 15 Years |
|---|---|---|
| Speciality | : | Gynaecologist... | Location | : | Indirapuram |
| Timings | : | Mon to Sat : 09:00 A... |

DR. SHEELA R
MBBS, MD(OBG & GNY)...
| Experience | : | 7+ Years |
|---|---|---|
| Speciality | : | Gynaecologist/Infert... | Location | : | HSR layout 2nd Sector |
| Timings | : | Mon to Sat : 9:45 AM... |

Copyright @ 2026,Apollo Cradle. All Rights Reserved
